Published: October 22, 2026 | Last Updated: October 22, 2026
Fire Injury First Aid Guide: Burns, Smoke, CO
Poisoning, CPR for Responders
Fire injuries do not stop when the flames go out. This fire injury first aid guide walks firefighters, factory responders and families through the practical steps that save lives: cooling burns, recognizing smoke poisoning, starting CPR and moving victims safely.
1. Fire Injury Types and Priorities
2. Burn Classification and Treatment
3. Chemical and Electrical Burns
4. Smoke Inhalation and CO Poisoning
5. CPR in Fire Scenarios
6. Burn Patient Transport
7. First Aid Kit for Fire Scenarios
8. Psychological First Aid
9. FAQ

Most fire deaths are not caused by burns. They are caused by smoke inhalation, carbon monoxide poisoning and delayed response. A person who walks out of a burning building looking fine can collapse ten minutes later from lung damage or heart rhythm concerns. The first responder who recognizes the warning signs early, starts the right treatment on scene and arranges transport to a burn center changes the outcome. This guide focuses on what to do in the first critical minutes, not on hospital level medicine. Every step here is something a trained responder or even a calm bystander can perform.
Before treating any injury, the first rule is scene safety. Do not become the next patient. A firefighter in full turnout gear and SCBA works inside; a civilian or factory first aider works outside the hot zone. Once the scene is safe, approach the victim, check responsiveness, shout for help and send someone to call emergency services. The burn treatment first aid sequence is always: stop the burning, cool the injury, cover the wound, then transport.

Burns are not all the same. A red sunburn on the shoulder and a white charred hand from a flash fire need completely different handling. Burn classification degrees decide whether you cool and cover on scene or load the victim immediately into an ambulance. The smoke inhalation treatment you give in the first five minutes is often more important than the burn dressing itself. This guide separates each injury type, tells you what it looks like, what to do and what never to do.
We also cover the injuries that people forget. Chemical burns continue eating skin until flushed. Electrical burns look small on the surface but cook muscle and bone underneath. Victims pulled from smoke can stop breathing without warning. A working fire first aid kit, the right burn patient transport technique, and basic CPR skills bridge the gap between the fire ground and the hospital door.
Read this guide before you need it. Practice the steps in training. Keep the kit stocked. When the alarm sounds, the goal is simple: stop the damage, keep the person breathing, get them to care. The sections below break each injury type into clear steps, tables and answers to the questions that come up on every fire ground.
Rescue teams staging at the edge of the scene wear their harness and carry a rope pack, because a structural collapse or a smoky stairwell may turn the rescue into a low angle evacuation.
A fire produces several injury mechanisms at once. Direct flame contact burns skin. Radiant heat cooks tissue from a distance. Hot gases and smoke injure the airway. Toxic gases poison blood and nerves. Falling debris crushes. Electricity shocks. Understanding which mechanism is acting on your patient decides the treatment order. A person with a small facial burn and black soot in the mouth is in more danger than a person with a large red arm burn and clear breathing. The fire injury first aid guide starts with this priority shift.
The primary survey follows the ABCDE pattern taught in every first aid course. Airway: is anything blocking the throat? Breathing: is the chest moving? Circulation: is there severe bleeding? Disability: is the person alert? Exposure: cut away burned clothing to see the full injury. In fire scenarios, airway and breathing come before bleeding. A person with soot on the face but no external burns can die from airway swelling while you are dressing a small hand wound.

The most frequent fire injuries are thermal burns from direct flame or hot surfaces, smoke inhalation from toxic gas, carbon monoxide poisoning, flash burns to the face and eyes, traumatic injury from falling debris or explosions, and electrical injury from downed power lines or faulty equipment. In industrial fires, chemical burns from spilled solvents, acids or corrosive materials add another layer. Each injury type demands a different immediate action. Thermal burns need cooling. Smoke inhalation needs oxygen and fresh air. Chemical burns need continuous flushing. Electrical injuries need cardiac monitoring. Treating all of them the same way is the classic on scene discrepancy.
When multiple victims are present, fire ground triage means sorting by urgency. Start with the walking wounded who can answer questions. Then move to anyone not breathing, then anyone with severe bleeding, then burn victims. A conscious person who can walk is lower priority than an unconscious person with soot in the airway. This sounds harsh, but mass casualty incidents demand it. For a single victim, the ABCDE survey takes thirty seconds and tells you what to treat first. Send a second person to call emergency services while you begin. For civilian responders, remember that you are not running a hospital. Your job is to stop the damage, support breathing and hand the patient to paramedics.
Tell the dispatcher the location, the number of victims, whether anyone is not breathing, whether the fire is still burning, and whether chemicals or electricity are involved. Give clear updates as the situation changes. Do not hang up until the dispatcher says you can. Clear communication between scene control and the ambulance crew reduces delay, and delay is what kills burn patients.
For the evacuation side of the story, see our high-rise fire escape guide covering building evacuation and smoke protection before rescuers arrive. Industrial teams should also review the factory fire safety guide on EHS risk assessment and emergency response planning that keeps incidents small. Buyers outfitting a first aid kit can start from our fire equipment buying guide.

Burn severity is classified by how deep the injury goes through the skin. The depth determines what it looks like, how much it hurts and whether it heals on its own or needs a skin graft. The burn classification degrees system runs from first degree, which is shallow and painful, to third degree, which destroys the full skin thickness. Knowing the difference tells you how to treat first-degree burns on scene and when a second- or third-degree patient must go to hospital immediately.
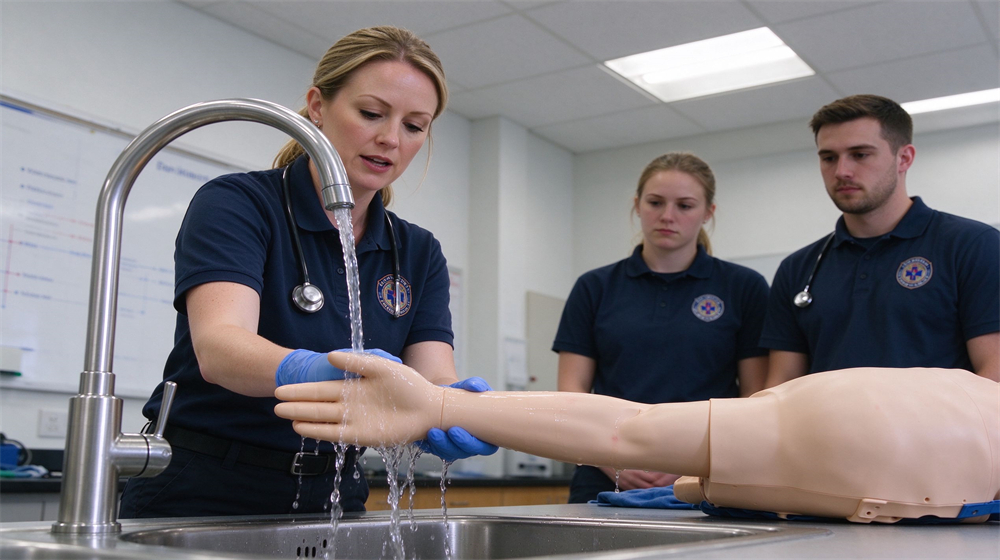
A first degree burn affects only the outer layer of skin. It looks red, dry and painful, like a mild sunburn. There are no blisters. The skin may swell slightly. When learning how to treat first-degree burns, the rule is simple: cool the area with cool running water for twenty minutes, then apply a clean dry dressing or leave it uncovered. Do not apply ice, butter, toothpaste, oil or any home remedy. Most first degree burns heal in three to seven days without medical care, but a first degree burn covering more than twenty percent of the body, or occurring in an infant or elderly person, still warrants medical attention.
A second degree burn goes deeper and forms blisters. The skin is red, raw, wet and extremely painful. Blisters may be intact or ruptured. This is the most common burn seen after a flash fire or hot liquid spill. Knowing how to treat second-degree burns starts with cooling: run cool water over the injury for twenty minutes, then cover with a sterile non adherent dressing.
Do not pop blisters. Do not apply ointments until a clinician evaluates the wound. Any second degree burn larger than the patient hand, or involving the face, hands, feet, genitals or a major joint, must go to a hospital. Second degree burns on the torso of an adult are more serious than the same size burn on the arm, because fluid loss across a large raw surface can cause shock.
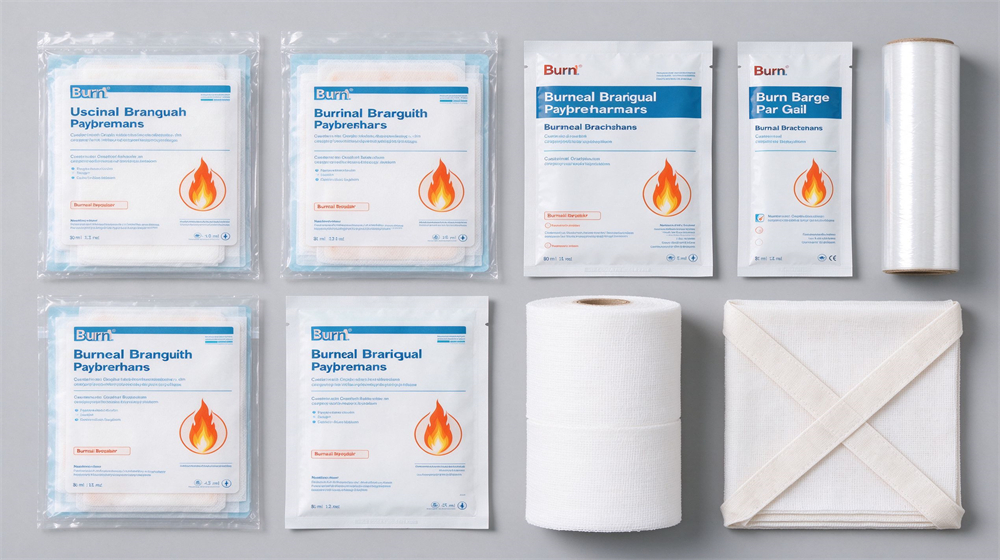
While waiting for the ambulance, a loose fire blanket over the dressing protects the wound from contamination and keeps the patient warm against the heat loss that burns cause.
A third degree burn destroys the full thickness of skin and may involve fat, muscle or bone underneath. The skin looks white, charred, leathery or dry brown. Surprisingly, it may not hurt much because the nerve endings have been destroyed. Third degree burns never heal on their own and require surgical care and skin grafting. On scene, do not immerse a large third degree burn in water for the full twenty minutes because this can cause hypothermia. Cool briefly, cover with a clean dry sheet, keep the patient warm and transport immediately. Any third degree burn of any size is a transport to hospital, period.
The Rule of Nines is a quick way to estimate what percentage of the body is burned. An adult head and neck equals nine percent. Each arm equals nine percent. The front of the torso equals eighteen percent. The back of the torso equals eighteen percent. Each front of leg equals nine percent and each back of leg equals nine percent. The genital area equals one percent. Add up the areas involved.
A burn covering more than fifteen percent in an adult, or ten percent in a child, means significant fluid loss and requires hospital fluid resuscitation. The Rule of Nines is an estimate, not a precise measurement, but it gives the receiving team a starting number. Tell the hospital the estimated percentage along with the depth and location.
Degree
Appearance
Pain
On Scene Treatment
Disposition
First
Red, dry, no blisters
Painful
Cool water 20 min, dry dressing
Home care if small
Second
Red, raw, blisters
Very painful
Cool water 20 min, non adherent dressing
Hospital if large or special area
Third
White, charred, leathery
Numb (nerves destroyed)
Cover with clean sheet, keep warm
Immediate transport
Fourth
Exposed muscle or bone
Numb
Cover, do not immerse, transport
Emergency burn center
|
Body Area |
Adult Percent |
Child Percent |
Quick Note |
|
Head and neck |
9% |
18% |
Child head is larger proportion |
|
Each arm |
9% |
9% |
Front and back combined |
|
Front torso |
18% |
18% |
Chest and abdomen |
|
Back torso |
18% |
18% |
Back and buttocks |
|
Each leg |
18% |
14% |
Front and back combined |
|
Genital area |
1% |
1% |
Perineum only |
Cooling is the single most effective on scene treatment for burns. Running cool running water for burns, not ice water, for twenty minutes stops the heat from continuing to cook deeper tissue. The earlier you cool, the less damage remains. This cooling step matches first aid guidance published by the Centers for Disease Control and Prevention (CDC).
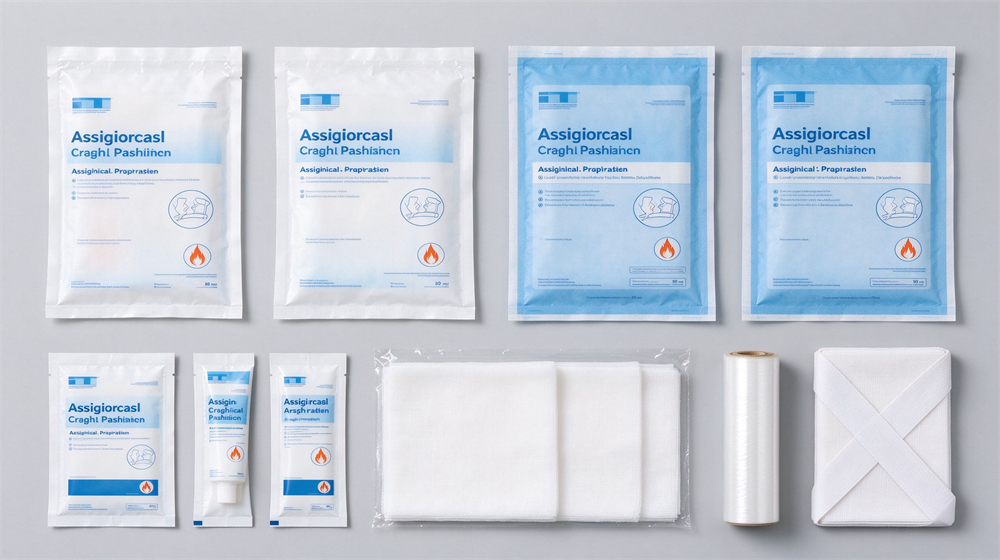
After twenty minutes, stop cooling because prolonged immersion drops body temperature. Cover with a sterile dressing, a clean sheet or cling film applied loosely. Never apply cotton, which sticks to the wound. Never apply butter, toothpaste, soy sauce or herbal remedies, which trap heat and cause infection. This burn treatment first aid sequence is simple but it is easy to forget under pressure.

Thermal burns are not the only burn seen at fires. Chemical and electrical burn first aid follows different rules from ordinary heat burns. Industrial sites, laboratories and even household cleaning supplies produce chemical burns that keep damaging skin until you flush them away. Downed power lines and faulty wiring cause electrical burns that look small outside but destroy tissue underneath. Both injury types demand specific on scene actions that differ from ordinary thermal burn care.

Acids, alkalis and solvents all burn skin, but alkalis such as cement, lye and ammonia penetrate deeper and keep damaging tissue longer. The first step in chemical burn treatment is to remove the source. Brush dry powder chemicals off the skin with a gloved hand before adding water, because water activates some powders. Then flush continuously with copious cool running water for at least twenty minutes.
Remove contaminated clothing carefully while flushing, taking care not to spread the chemical to unexposed skin. Do not apply neutralizing agents, because the chemical reaction generates extra heat. Bring the chemical container or safety data sheet to the hospital so clinicians know what they are dealing with. Eye exposure requires continuous eyelid-flushing and immediate ophthalmology review.
On the fire ground, chemical burns often accompany structural fires at industrial plants. A responder wearing full PPE and SCBA can approach; a civilian should stay upwind and uphill. Once the victim is decontaminated, the burn is treated like any other thermal burn: cover with sterile dressing, monitor airway and transport. Document the chemical name and estimated exposure time for the hospital. This detail changes the fluid management and the choice of antidote if the chemical has systemic effects.
Electrical injuries are deceptive. The entry and exit wounds look small, but the current has passed through the body and cooked muscle, blood vessels and heart tissue underneath. The first rule in electrical burn first aid is power safety before touch. Do not touch a person still in contact with an energized wire. Shut off the breaker, use a dry wooden stick or insulating material to push the wire away, or wait for the power company.
Once the power is off, check the breathing and pulse immediately. Electrical shock commonly causes cardiac arrest, so be ready to start CPR. Even if the victim is awake and walking, transport them to hospital. The heart can develop arrhythmia hours after the shock. Look for entry and exit wounds on opposite sides of the body, because internal damage tracks between them. Immobilize the spine if the victim was thrown by the force of the shock.
Lightning injury is a special case. The current is massive but the duration is short. Victims of a lightning strike are safe to touch immediately because they do not carry a charge. Start CPR on anyone not breathing, because lightning frequently causes respiratory arrest that lasts minutes. Most lightning victims survive if breathing is supported quickly. Keep the patient supine, monitor breathing and transport. This is one of the few fire ground scenarios where starting CPR immediately on an apparently lifeless person has a high success rate.
|
Type |
First Action |
Flushing |
Key Danger |
Transport |
|
Acid burn |
Remove clothing, brush powder |
Water 20 min minimum |
Deep tissue penetration |
Hospital always |
|
Alkali burn |
Remove clothing, brush powder |
Water 30 min or longer |
Continued damage for hours |
Burn center |
|
Solvent burn |
Remove contaminated PPE |
Water flush, prevent spreading |
Skin absorption and inhalation |
Hospital |
|
Electrical |
Cut power, do not touch victim |
Not needed for surface |
Cardiac arrest, internal burns |
Hospital always |

Smoke inhalation is the leading cause of death in structure fires. A person can survive the flames but die from a swollen airway, toxic gas in the blood or lack of oxygen. The tricky part is that symptoms may not appear for hours. A firefighter or occupant who walks out coughing but looks fine can lose consciousness in the parking lot. The smoke inhalation treatment starts the moment you recognize the signs, not when the person collapses.

Look for soot around the mouth and nose, singed nasal hairs, burned facial hair, hoarse or whispered voice, dry cough, black or gray sputum, shortness of breath, rapid breathing, headache, confusion, dizziness, cherry red skin color, altered mental state or a racing pulse. Any one of these in someone pulled from a smoke filled building is enough to assume airway injury. Even a survivor who feels normal after escaping should be given fresh air and monitored. Carbon monoxide, the most common toxic product of combustion, binds to hemoglobin two hundred times more tightly than oxygen, carbon monoxide poisoning starving the brain and heart.
When learning how to treat smoke inhalation, the first move is simple: move the victim into fresh air immediately. Loosen tight clothing around the neck and chest. If available, give high concentration oxygen through a non rebreather mask at the highest flow rate. First aid actions for smoke exposure follow guidance from the American Red Cross. Keep the victim calm and sitting upright, because lying flat worsens breathing effort. Monitor the voice and breathing every few minutes. If the voice gets more hoarse or breathing becomes labored, the airway is swelling and emergency intubation may be needed. Do not give food or drink because swelling may make swallowing unsafe. This is the core smoke inhalation treatment that any trained responder can deliver on scene.

Burning plastics, wool, silk and synthetic materials release hydrogen cyanide. Cyanide stops cells from using oxygen, causing rapid collapse, seizures and death even at low concentrations. Signs include sudden loss of consciousness, seizures, deep rapid breathing and a faint almond smell that most people cannot detect. In enclosed space fires, cyanide poisoning is suspected in anyone who collapses quickly without obvious burns. Modern fire service carries cyanide antidote kits, but civilian first aid focuses on rapid removal to fresh air, oxygen and immediate transport. Carbon monoxide from any fire, and hydrogen chloride from burning PVC, also injure the airway and lungs. Every victim pulled from an enclosed fire should be evaluated in hospital with blood gas and carboxyhemoglobin testing.
Pulse oximetry is unreliable in smoke victims because it cannot distinguish carbon monoxide hemoglobin from normal hemoglobin. A normal reading on a fingertip monitor can be falsely reassuring. Hospital blood gas analysis is required. On scene, trust your eyes and ears: hoarse voice, soot, breathing difficulty and altered mental state are enough to transport regardless of the monitor number.

Cardiac arrest in a fire setting is usually caused by hypoxia from smoke inhalation, not by a heart attack. That changes the CPR approach. For an ordinary street cardiac arrest, hands only CPR may be acceptable. For a fire victim, rescue breaths matter because the cause is lack of oxygen. CPR fire emergency response combines chest compressions, rescue breaths and early AED use, all delivered in the smoke free zone away from the hazard.
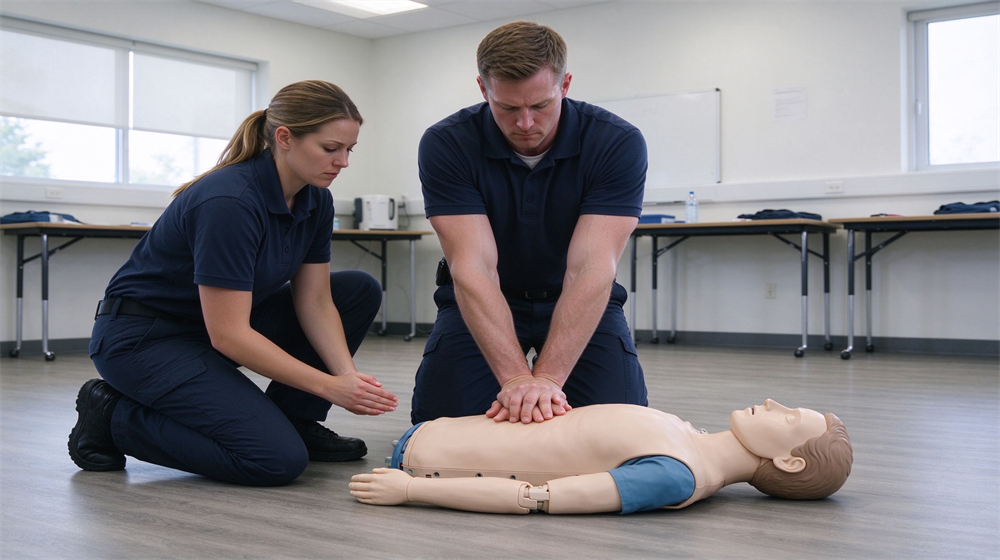
After moving the victim to safe ground, tap the shoulder and shout. If there is no response and no normal breathing, start CPR immediately. Send someone to call emergency services and fetch an AED. Do not spend time checking a pulse for more than ten seconds. If you are unsure whether there is a pulse, start compressions. For a fire victim, tilt the head back, lift the chin, check for breathing for no more than five seconds. If the chest does not rise, give two rescue breaths, then start thirty compressions by two breaths. Continue until the person wakes up, professional help arrives, or you are physically exhausted.
Kneel beside the victim. Place the heel of one hand on the center of the chest, between the nipples. Place the other hand on top, interlock fingers. Keep arms straight and shoulders directly above the hands. Compress at least five centimeters but no more than six centimeters, at a rate of one hundred to one hundred twenty per minute. Let the chest fully recoil between chest compressions for CPR. Minimize interruptions to less than ten seconds. Two person CPR lets one person compress while the other gives breaths and manages the airway. Swap roles every two minutes to limit fatigue. The quality of compressions decays fast, and tired compressions do not pump blood effectively.

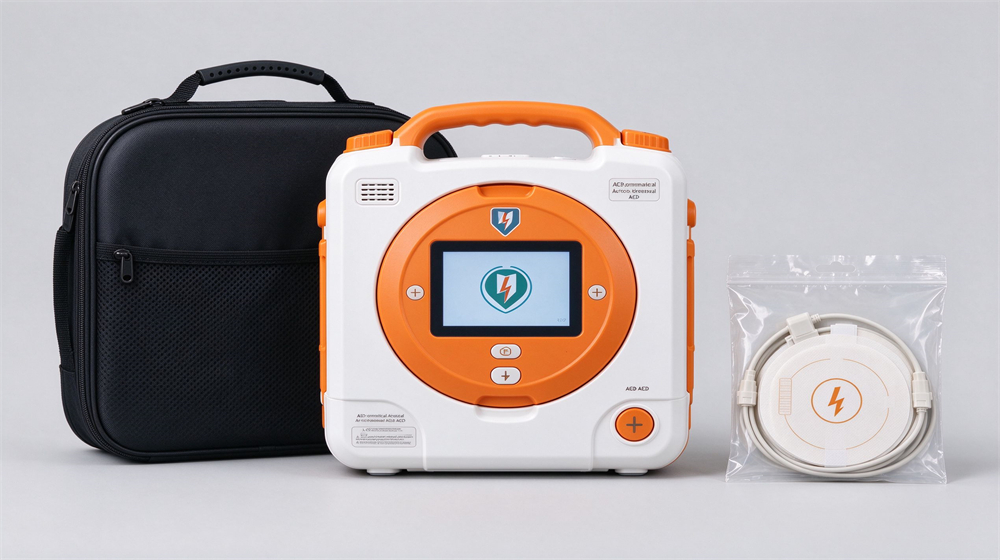
As soon as an AED arrives, turn it on and follow the voice prompts. Expose the chest, wipe it dry if wet or sweaty, and apply the pads to the bare chest as shown on the diagram. One pad goes on the upper right chest below the collarbone, the other on the lower left side beside the armpit. Make sure no one is touching the victim when the device says it is analyzing. If a shock is advised, clear the victim and press the shock button.
Immediately resume compressions after the shock. If no shock is advised, resume compressions right away. AEDs are safe on burn victims as long as the chest is dry. Do not place pads over charred skin or metal jewelry. Cut away clothing if needed. The CPR fire emergency chain works most effectively when compressions start within seconds and the AED arrives within minutes.
For infants and children, the compression depth is shallower and the ratio changes, but fire victims are usually adults. If you are alone with an adult victim, call emergency services first before starting CPR, because adult cardiac arrest is usually a heart rhythm concern that needs a defibrillator. In fire scenarios, however, the cause is hypoxia, so giving two rescue breaths early matters more than in an ordinary cardiac arrest.
Getting a burn victim from the fire ground to the hospital safely is as important as the on scene treatment. A poorly handled transport can break an airway, worsen a burn, or cause shock. Burn patient transport follows a few simple rules that prevent secondary injury. The goal is to move the person without rubbing burned skin, without bending burned joints, and without losing body heat.

Move a burn victim only when the scene is unsafe or when professional transport has arrived. If the building is still burning or the structure is unstable, move the person to fresh air first. Do not drag a burned person across rough ground. Use a stretcher, a sheet, or a rescue blanket to lift. If spinal immobilization is needed, secure the neck and spine before moving. Two to four rescuers lift in unison on a counted command. Never pull an arm or a leg to drag someone. Burned skin sticks to clothing and separates easily.
Do not pull burned clothing off. Cut around it with trauma shears. If fabric sticks to a wound, leave it. Cover burned areas with a sterile non adherent dressing, a clean sheet or loosely applied cling film. Do not wrap burned fingers or toes together, because they may stick as they heal. Keep the victim warm with a blanket over the dressing, because burns cause massive heat loss and hypothermia kills. Give small sips of water only if the victim is fully alert and going to hospital within an hour. If the person is confused, has facial burns, or may need surgery, do not give anything by mouth because anesthesia will be needed.

Load the stretcher into the ambulance with the feet toward the rear if transport is long, so the head is lower for circulation. Keep the victim supine or slightly elevated if breathing is labored. Tell the paramedic the time of injury, the estimated burn percentage using the Rule of Nines, the depth, the mechanism, whether smoke was inhaled, and any first aid given. This handover information determines the hospital fluid rate and whether the person goes straight to the burn center. Write it down if possible, because stress makes memory unreliable. For a detailed look at the equipment used in rescue and transport, see the firefighter turnout gear page and the escape rope and harness page.

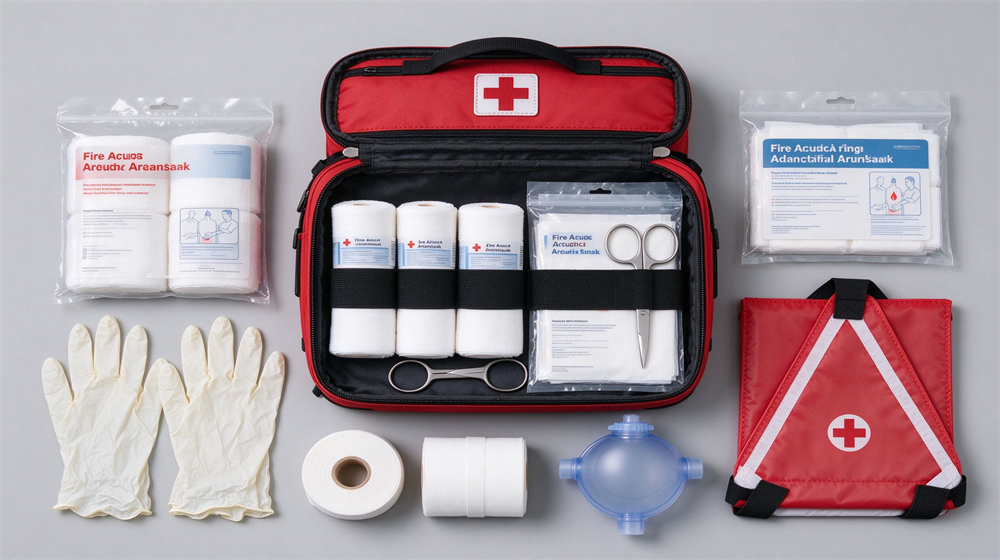
A fire first aid kit that sits in a cabinet and is never checked is worse than no kit, because it gives false confidence. A working fire first aid kit is stocked, dated, and placed where responders can reach it in seconds. The contents depend on whether the kit lives on a fire truck, in a factory medical room, or under a kitchen sink at home. The principle is the same: the kit must match the injuries you actually expect. For example, flood rescue equipment list and emergency response guide.
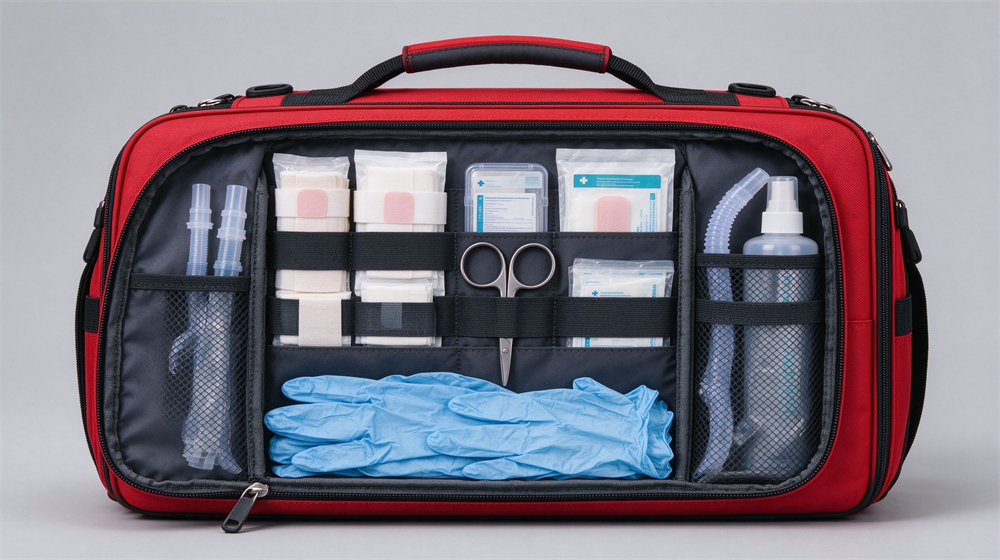
Every fire first aid kit should contain nitrile gloves for body fluid protection, a pocket CPR mask with a one way valve, sterile non adherent dressings in multiple sizes, burn dressing sheets, cling film or clean plastic wrap, triangular bandages for slings, gauze rolls, trauma shears, saline bottles for irrigation, a thermal blanket, and a notepad to record the handover. Advanced kits add an AED automated external defibrillator, a portable oxygen cylinder with mask, airway adjuncts, a cervical collar, a scoop stretcher or vacuum mattress, and a burn reference chart. For factory and station kits, also include a copy of the site chemical list and emergency contact numbers.
A basic home kit handles small burns, cuts and bandaging. A factory medical room kit should support multiple victims and include oxygen and AED. A fire apparatus trauma bag is built for responders who already wear PPE and need compact, fast access gear. The table below compares the three tiers. Stocking the right tier prevents the common consideration of opening a kit on scene and finding nothing useful for the actual injury.
|
Item |
Home Basic |
Factory Advanced |
Apparatus Trauma |
|
Gloves and mask |
Yes |
Yes, multiple pairs |
Yes, heavy duty |
|
Burn dressings |
Small pack |
Multiple sizes |
Sheets and gel |
|
AED |
No |
Recommended |
Standard |
|
Oxygen kit |
No |
Yes |
Yes |
|
Trauma shears |
Small scissors |
Yes |
Yes |
|
Thermal blanket |
One |
Multiple |
Two |
|
Cervical collar |
No |
Yes |
Yes |
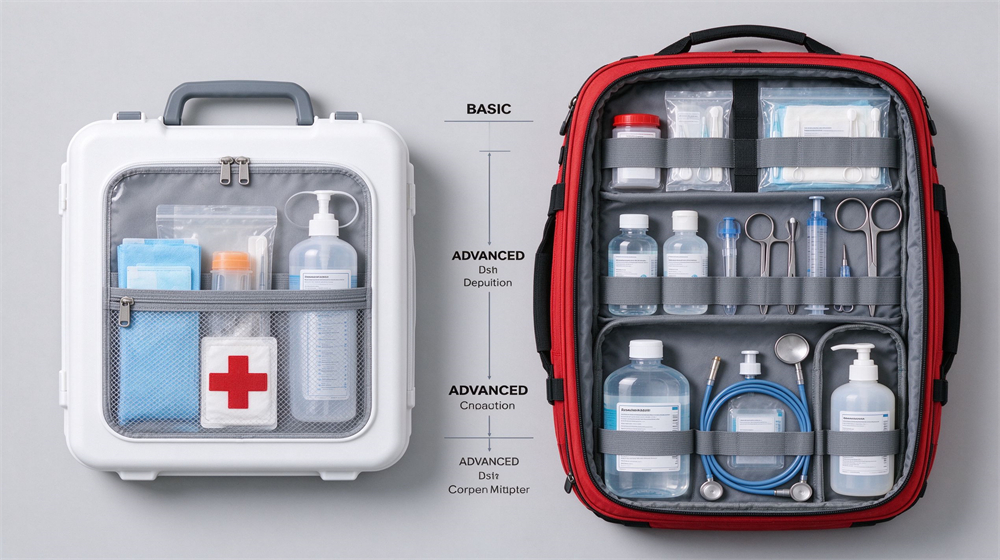
Check the kit monthly. Look at expiration dates on dressings, gloves and oxygen cylinders. Confirm the AED battery indicator is green and the pads are in date. Replace anything used after an incident. A kit missing half its supplies falls short exactly when it is needed. For related equipment, see the SCBA page, the fire helmet page and the gloves and boots page.

Burns and smoke are not the only injuries after a fire. Survivors, neighbors and even firefighters themselves carry psychological wounds that show up later: nightmares, jumpiness, withdrawal, guilt, panic. Psychological first aid is the simple on scene support that reduces the chance these reactions turn into long term post traumatic stress. It does not require a psychology degree. It requires calm presence, listening and helping people feel safe. For example, disaster emergency lighting kit for post-fire rescue operations.

Normal reactions after a fire include shaking, crying, confusion, rapid speech, silence, nausea or a sense of unreality. These are not signs of weakness. They are the normal body response to extreme stress. Most people settle within hours or days. Watch for people who seem completely numb, who cannot stop repeating the event, who cannot sleep for more than a few nights, or who withdraw from everything that reminds them of the fire. Those people need professional follow up, not just a comforting word on scene.
Stay close but do not crowd. Speak in a calm low voice. Tell people what is happening and what help is coming. Help them find family, a coat, water and a safe place to sit. Do not force them to talk about what they saw. Do not say it could have been worse or that everything happens for a reason. Just listen. Practical help often matters more than emotional words: a blanket, a phone call to a relative, directions to the shelter. For children, keep them with a familiar adult and keep them from seeing gruesome scenes. For elderly or disabled survivors, arrange transport because they cannot manage on their own.

Firefighters and factory response crews also need support. A short debrief after a major incident, held within twenty four to seventy two hours, lets the team talk through what happened, what went differently and what they felt. This is not a therapy session. It is a structured checkin led by a supervisor or peer support person. Workplace traumatic stress resources are published by NIOSH.
Watch team members who are unusually quiet, who stop working, or who joke constantly after a traumatic event. Offer professional counseling without shame. Most fire services and industrial safety programs have employee assistance programs. Referring a colleague early prevents a crisis months later. The physical kit gets checked monthly; the mental kit needs the same attention.

Below are the practical fire injury first aid questions firefighters, factory medical officers and families ask when they bring this guide back to their own site. Each answer points to the key on scene step and the equipment choice that backs it up.

Remove the person from the heat source safely, then cool the burn with cool running water for at least twenty minutes. Do not use ice, butter, toothpaste or ointments. Cover with a sterile non sticking dressing and seek medical help for any burn larger than a hand or involving the face, hands, feet, joints or genitals.
Any burn that is white, charred or leathery is a third degree burn and needs emergency transport. Burns that blister, are larger than the victim hand, or involve the face, airway, hands, feet, genitals or major joints also need urgent hospital care. Chemical and electrical burns always need medical evaluation even if the surface looks small.
No. Intact blisters protect the wound from infection. Popping them increases the risk of sepsis. Leave blisters alone, cover loosely with a sterile dressing and let a clinician decide whether to drain them.
The Rule of Nines estimates body surface area burned: head nine percent, each arm nine percent, each front of leg eighteen percent, back of leg eighteen percent, front trunk eighteen percent, back trunk eighteen percent and genital area one percent. Use it to triage severity and communicate the estimate to the receiving hospital.
Remove contaminated clothing, brush dry powder chemicals off the skin before wetting, then flush continuously with copious cool water for at least twenty minutes. Do not try to neutralize the chemical with another substance. Bring the chemical container or safety data sheet to the hospital.
First cut the power or use a non conductive object to separate the victim from the source. Never touch a person still in contact with electricity. Electrical burns can look small on the surface but cause deep tissue damage and cardiac arrhythmia inside. Transport every electrical injury to hospital.
Signs include soot around the mouth or nose, singed nasal hairs, hoarse voice, cough with black sputum, shortness of breath, headache, confusion, cherry red skin or altered mental state. Any survivor pulled from a smoke filled space should be given oxygen and monitored, even if they feel fine.

Carbon monoxide is odorless and colorless. Levels above ten percent saturation cause headache and confusion, above thirty percent cause dizziness and weakness, and above fifty percent can cause loss of consciousness and death. Anyone exposed to smoke should have carbon monoxide levels checked in hospital.
Check for responsiveness and breathing. If the person is unresponsive and not breathing or breathing abnormally, call emergency services and start chest compressions immediately. In fire scenarios, also give rescue breaths because hypoxia from smoke is often the cause of arrest.
For adults, compress the center of the chest at least five centimeters but no more than six centimeters, at a rate of one hundred to one hundred twenty compressions per minute. Allow full chest recoil between compressions. Minimize interruptions.
Yes. Dry the chest completely before applying AED pads. Cut away clothing if needed. Follow the voice prompts. If the person is wet or covered in sweat, wipe the chest dry because moisture can cause arcing. AED use is safe on burn victims.
Do not peel burned clothing that sticks to skin. Cut around it. Do not apply pressure to burned areas. Use a clean sheet or sterile dressing to cover the victim before moving. Keep the victim warm because burns cause heat loss. If spinal injury is possible, immobilize the neck.
At minimum: sterile burn dressings, non adherent gauze, cling film or clean plastic wrap, triangular bandages, gloves, scissors, CPR mask, saline bottles, a thermal blanket and a pocket mask. Advanced kits add an AED, oxygen cylinder, airway kit and trauma shears.
Inspect contents monthly. Check expiration dates on dressings, oxygen cylinders and AED pads. Replace any used item immediately after an incident. A kit that is missing supplies or out of date is equivalent to having no kit.
Psychological first aid means staying calm, listening without judgment, helping people feel safe, connecting them to practical support and encouraging them to talk to family or professional counselors. Do not force people to relive the event. Watch for persistent nightmares, withdrawal or panic that lasts more than a few weeks.
Transport immediately for: third degree burns of any size, burns to face hands feet joints or genitals, suspected smoke inhalation, chemical or electrical burns, burns covering more than ten percent of the body, any unconscious or confused victim, and any victim with difficulty breathing.
Medical Disclaimer: This article is provided for first aid training and educational reference only. It does not replace professional medical advice, diagnosis or treatment. In any fire injury emergency, call your local emergency number immediately. Always seek the guidance of qualified medical personnel for serious burns, smoke inhalation, chemical exposure, electrical injury or cardiac arrest. Never delay professional care to apply techniques described here.

YRF Fire Safety and First Aid Program
This guide supports fire departments, factory emergency response teams, school safety officers and household first aid preparedness. Related equipment pages cover turnout gear, SCBA, helmets, fire blankets, escape ropes and gloves and boots.
Дружні посилання :
Авторське право © Custom Disaster - Relief Bedding: Tents, Sleeping Bags, Blankets Всі права захищені
професійна команда для обслуговування !










